Pediatric Supracondylar Humerus Fracture Repair with Mini-Open Assisted Reduction and Percutaneous Pinning
Emily S. Powis, BS1; Donald L. Fejfar, MD1; Nikhil Gattu, MD1; Samhita Kadiyala, BA1; Elizabeth Rich, MD2; Wesley Kalomba, MD3; Hizkyas Kassaye, MD4; Ridwan M. Saeed, MD5; Bitiel Banda, MD6; Pierre M. Woolley, MD7; Kiran J. Agarwal-Harding, MD, MPH1,8
1Harvard Global Orthopaedics Collaborative, Boston, MA
2Walter Reed National Military Medical Center, Bethesda, MD
3Lilongwe Institute of Orthopaedics and Neurosurgery, Lilongwe, Malawi
4Hawassa University Comprehensive Specialized Hospital, Hawassa, Ethiopia
5Muhimbili Orthopaedic Institute, Dar es Salaam, Tanzania
6Mzuzu Central Hospital, Mzuzu, Malawi
7Hôpital Universitaire La Paix, Port au Prince, Haiti
8Beth Israel Deaconess Medical Center, Boston, MA
Supracondylar humerus (SCH) fractures are the most common elbow fractures in children and represent a significant source of morbidity in low- and middle-income countries (LMICs), where delayed presentation and limited surgical capacity frequently lead to poor outcomes. Closed reduction and percutaneous pinning (CRPP) is the gold-standard treatment for displaced SCH fractures and is particularly well-suited to resource-limited settings given its reliance on minimal, low-cost implants.
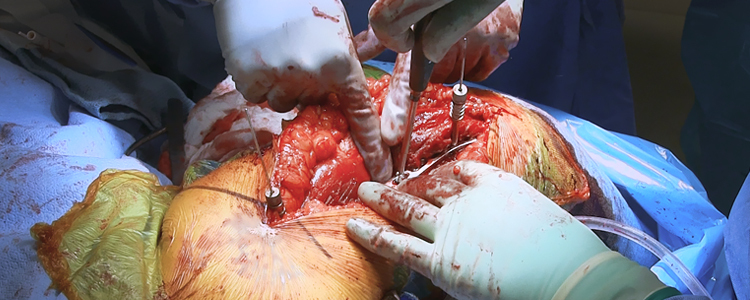
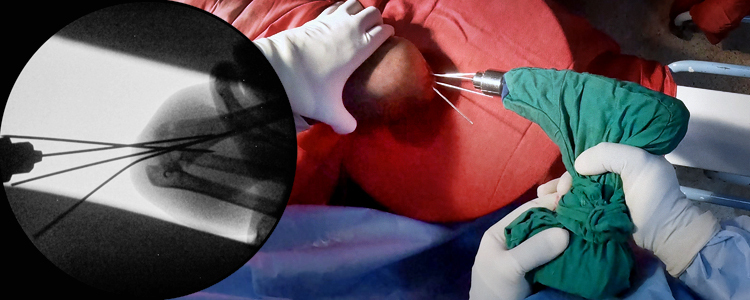
This case describes a 9-year-old male who presented to Mzuzu Central Hospital in Malawi with a completely displaced Gartland Type III SCH fracture following a fall. Surgical intervention was delayed three days due to unavailability of intraoperative fluoroscopic imaging. Neurovascular examination was intact on presentation. The procedure was performed under general anesthesia. Reduction was first attempted with longitudinal traction to unlock the distal fragment, followed by thumb pressure on the olecranon and elbow flexion. As the distal fragment remained incompletely reduced in the sagittal plane, a small posterior incision was made and the Kapandji maneuver was performed to achieve satisfactory reduction, confirmed fluoroscopically. Three smooth Kirschner wires (K-wires) were introduced in retrograde fashion from the lateral condyle under fluoroscopic guidance. One of the three K-wires was intramedullary and became loose prior to case conclusion, so it was removed before the remaining pins were cut and bent outside the skin, and a posterior back slab was applied with the elbow at 90 degrees of flexion. The remaining K-wires were removed at 4 weeks, and range-of-motion exercises were initiated thereafter.
This case demonstrates that percutaneous pinning, with mini-open assistance where closed reduction cannot be achieved, can be performed safely in resource-limited settings and illustrates the real-world intraoperative challenges, including limited C-arm resolution, use of non-orthopaedic drills with insufficient power, and bent K-wires, that afflict much of the developing world.