Tag Archives: pediatric

PUBLISHED: Pediatric Supracondylar Humerus Fracture Repair with Mini-Open Assisted Reduction and Percutaneous Pinning

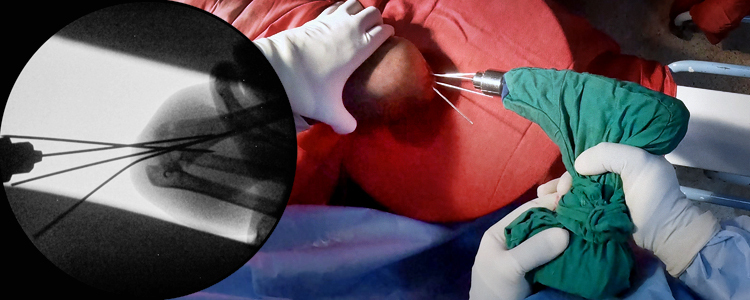
Pediatric Supracondylar Humerus Fracture Repair with Mini-Open Assisted Reduction and Percutaneous Pinning
Emily S. Powis, BS1; Donald L. Fejfar, MD1; Nikhil Gattu, MD1; Samhita Kadiyala, BA1; Elizabeth Rich, MD2; Wesley Kalomba, MD3; Hizkyas Kassaye, MD4; Ridwan M. Saeed, MD5; Bitiel Banda, MD6; Pierre M. Woolley, MD7; Kiran J. Agarwal-Harding, MD, MPH1,8
1Harvard Global Orthopaedics Collaborative, Boston, MA
2Walter Reed National Military Medical Center, Bethesda, MD
3Lilongwe Institute of Orthopaedics and Neurosurgery, Lilongwe, Malawi
4Hawassa University Comprehensive Specialized Hospital, Hawassa, Ethiopia
5Muhimbili Orthopaedic Institute, Dar es Salaam, Tanzania
6Mzuzu Central Hospital, Mzuzu, Malawi
7Hôpital Universitaire La Paix, Port au Prince, Haiti
8Beth Israel Deaconess Medical Center, Boston, MA

Supracondylar humerus (SCH) fractures are the most common elbow fractures in children and represent a significant source of morbidity in low- and middle-income countries (LMICs), where delayed presentation and limited surgical capacity frequently lead to poor outcomes. Closed reduction and percutaneous pinning (CRPP) is the gold-standard treatment for displaced SCH fractures and is particularly well-suited to resource-limited settings given its reliance on minimal, low-cost implants.

This case describes a 9-year-old male who presented to Mzuzu Central Hospital in Malawi with a completely displaced Gartland Type III SCH fracture following a fall. Surgical intervention was delayed three days due to unavailability of intraoperative fluoroscopic imaging. Neurovascular examination was intact on presentation. The procedure was performed under general anesthesia. Reduction was first attempted with longitudinal traction to unlock the distal fragment, followed by thumb pressure on the olecranon and elbow flexion. As the distal fragment remained incompletely reduced in the sagittal plane, a small posterior incision was made and the Kapandji maneuver was performed to achieve satisfactory reduction, confirmed fluoroscopically. Three smooth Kirschner wires (K-wires) were introduced in retrograde fashion from the lateral condyle under fluoroscopic guidance. One of the three K-wires was intramedullary and became loose prior to case conclusion, so it was removed before the remaining pins were cut and bent outside the skin, and a posterior back slab was applied with the elbow at 90 degrees of flexion. The remaining K-wires were removed at 4 weeks, and range-of-motion exercises were initiated thereafter.

This case demonstrates that percutaneous pinning, with mini-open assistance where closed reduction cannot be achieved, can be performed safely in resource-limited settings and illustrates the real-world intraoperative challenges, including limited C-arm resolution, use of non-orthopaedic drills with insufficient power, and bent K-wires, that afflict much of the developing world.
PUBLISHED: Ultrasound-Guided Paravertebral Block in an Infant

Ultrasound-Guided Paravertebral Block in an Infant
Jun Takeshita, MD, PhD
Osaka Women’s and Children’s Hospital

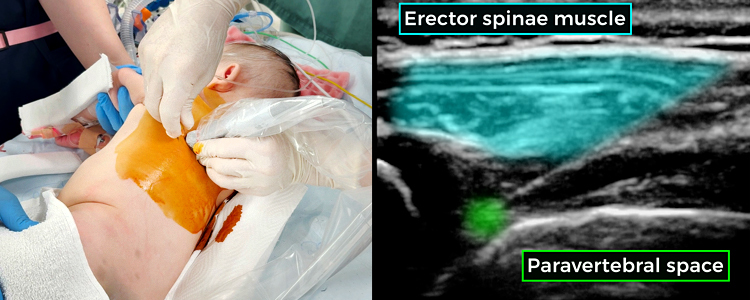
Thoracic paravertebral block (PVB) is a regional anesthetic technique wherein a local anesthetic is injected into the thoracic paravertebral space to produce a unilateral blockade of the spinal nerves and sympathetic chain. It provides effective analgesia after unilateral thoracic surgery and may reduce perioperative opioid requirements. Ultrasound guidance facilitates identification of the transverse process, superior costotransverse ligament, pleura, and needle trajectory, and allows accurate local anesthetic deposition.

This video demonstrates a left-sided, ultrasound-guided thoracic PVB at the fourth thoracic level in a 4-month-old, 7.6-kg male infant undergoing division of the vascular ring through a left fourth intercostal thoracotomy. The video underscores the identification of the relevant sonoanatomy, continuous visualization of the true needle tip, avoidance of the pleura and intercostal vessels, and careful advancement of the needle into the thoracic paravertebral space. A total of 3.8 mL of 0.25% ropivacaine was administered, corresponding to a dosage of 0.5 mL/kg and 1.23 mg/kg. The block was successfully performed without immediate block-related complications and provided effective perioperative analgesia for the thoracotomy. This video presents practical considerations for safe and reliable ultrasound-guided thoracic PVB in infants and young children.

PUBLISHED: Ultrasound-Guided Rectus Sheath Block in a Pediatric Patient

Ultrasound-Guided Rectus Sheath Block in a Pediatric Patient
Jun Takeshita, MD, PhD
Osaka Women’s and Children’s Hospital

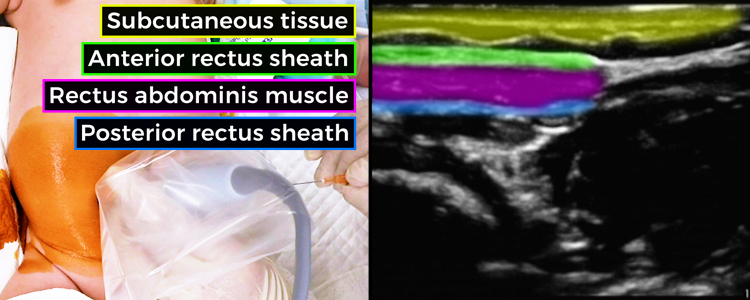
Rectus sheath block (RSB) is a regional anesthesia technique in which a local anesthetic is injected between the posterior aspect of the rectus abdominis muscle and the posterior rectus sheath to block the anterior cutaneous branches of the thoracoabdominal nerves. In pediatric patients, RSB is particularly useful for surgeries performed through umbilical or circumumbilical incisions, such as umbilical hernia repair, laparoscopic surgery with umbilical port placement, pyloromyotomy for hypertrophic pyloric stenosis, and surgery for duodenal atresia, intestinal malrotation, or ovarian cysts. Ultrasound guidance improves the precision and safety of the block by enabling direct visualization of the rectus abdominis muscle, posterior rectus sheath, and underlying peritoneum.

This video demonstrates ultrasound-guided bilateral RSB in a 27-day-old, 3.9-kg neonate undergoing circumumbilical pyloromyotomy for hypertrophic pyloric stenosis. The video highlights the key technical aspects of the procedure, including the identification of the posterior rectus sheath, continuous visualization of the needle tip, appropriate lateral placement of the local anesthetic within the posterior rectus sheath plane, and measures to avoid peritoneal puncture and vascular injury. Particular attention is also given to the conservative dosing of ropivacaine in neonates to minimize the risk of local anesthetic systemic toxicity.

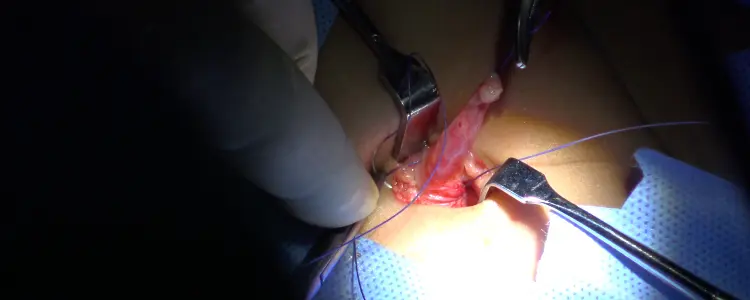
PUBLISHED: Pediatric Infant Bilateral Open Inguinal Hernia Repair – Twin A

Pediatric Infant Bilateral Open Inguinal Hernia Repair – Twin A
Shai I. B. Stewart, MD1; Lissa Henson, MD2; Domingo Alvear, MD3
1Howard University Hospital
2Philippine Society of Pediatric Surgeons
3World Surgical Foundation

An inguinal hernia (IH) is a protrusion of intra-abdominal contents through the inguinal canal that can arise at any time from infancy to adulthood. It is more common in males with a lifetime risk of 27% as compared to 3% in females. Most pediatric IHs are congenital and caused by failure of the peritoneum to close, resulting in a patent processus vaginalis (PPV). IH present as a bulge in the groin area that can become more prominent when crying, coughing, straining, or standing up, and disappears when lying down. Diagnosis is based on a thorough medical history and physical examination, but imaging tests such as ultrasound can be used when the diagnosis is not readily apparent. IHs are generally classified as indirect, direct, and femoral based on the site of herniation relative to surrounding structures. Indirect hernias protrude lateral to the inferior epigastric vessels, through the deep inguinal ring. Direct hernias protrude medial to the inferior epigastric vessels, within Hesselbach’s triangle. Femoral hernias protrude through the small and inflexible femoral ring. In infants and children, IH are always operated on to prevent incarceration.

Surgical correction in infants and children is done by high ligation of the hernia sac only, called a herniotomy. Here, we present a female infant with bilateral IH. Upon exploration, a hernia sac was found, and ligation was performed bilaterally. In female patients, it is believed that failure of the closure of the canal of Nuck alongside the round ligament of the uterus is the etiology. Oftentimes there is a “sliding hernia” where the ovary and or the fallopian tube is attached to the sac, sometimes the uterus itself is attached.