Tag Archives: fracture

PUBLISHED: Pediatric Supracondylar Humerus Fracture Repair with Mini-Open Assisted Reduction and Percutaneous Pinning

Pediatric Supracondylar Humerus Fracture Repair with Mini-Open Assisted Reduction and Percutaneous Pinning
Emily S. Powis, BS1; Donald L. Fejfar, MD1; Nikhil Gattu, MD1; Samhita Kadiyala, BA1; Elizabeth Rich, MD2; Wesley Kalomba, MD3; Hizkyas Kassaye, MD4; Ridwan M. Saeed, MD5; Bitiel Banda, MD6; Pierre M. Woolley, MD7; Kiran J. Agarwal-Harding, MD, MPH1,8
1Harvard Global Orthopaedics Collaborative, Boston, MA
2Walter Reed National Military Medical Center, Bethesda, MD
3Lilongwe Institute of Orthopaedics and Neurosurgery, Lilongwe, Malawi
4Hawassa University Comprehensive Specialized Hospital, Hawassa, Ethiopia
5Muhimbili Orthopaedic Institute, Dar es Salaam, Tanzania
6Mzuzu Central Hospital, Mzuzu, Malawi
7Hôpital Universitaire La Paix, Port au Prince, Haiti
8Beth Israel Deaconess Medical Center, Boston, MA

Supracondylar humerus (SCH) fractures are the most common elbow fractures in children and represent a significant source of morbidity in low- and middle-income countries (LMICs), where delayed presentation and limited surgical capacity frequently lead to poor outcomes. Closed reduction and percutaneous pinning (CRPP) is the gold-standard treatment for displaced SCH fractures and is particularly well-suited to resource-limited settings given its reliance on minimal, low-cost implants.

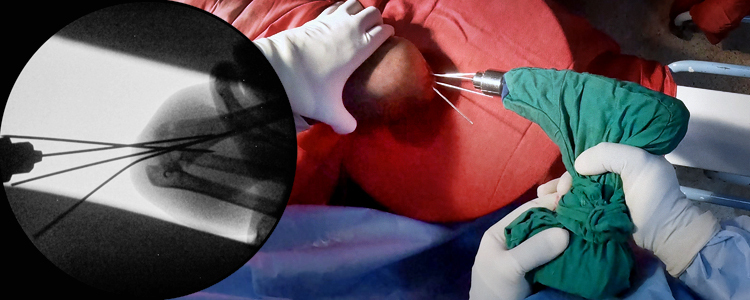
This case describes a 9-year-old male who presented to Mzuzu Central Hospital in Malawi with a completely displaced Gartland Type III SCH fracture following a fall. Surgical intervention was delayed three days due to unavailability of intraoperative fluoroscopic imaging. Neurovascular examination was intact on presentation. The procedure was performed under general anesthesia. Reduction was first attempted with longitudinal traction to unlock the distal fragment, followed by thumb pressure on the olecranon and elbow flexion. As the distal fragment remained incompletely reduced in the sagittal plane, a small posterior incision was made and the Kapandji maneuver was performed to achieve satisfactory reduction, confirmed fluoroscopically. Three smooth Kirschner wires (K-wires) were introduced in retrograde fashion from the lateral condyle under fluoroscopic guidance. One of the three K-wires was intramedullary and became loose prior to case conclusion, so it was removed before the remaining pins were cut and bent outside the skin, and a posterior back slab was applied with the elbow at 90 degrees of flexion. The remaining K-wires were removed at 4 weeks, and range-of-motion exercises were initiated thereafter.

This case demonstrates that percutaneous pinning, with mini-open assistance where closed reduction cannot be achieved, can be performed safely in resource-limited settings and illustrates the real-world intraoperative challenges, including limited C-arm resolution, use of non-orthopaedic drills with insufficient power, and bent K-wires, that afflict much of the developing world.
PUBLISHED: Left Tibia Pilon Open Fracture Open Reduction and Internal Fixation with External Fixator

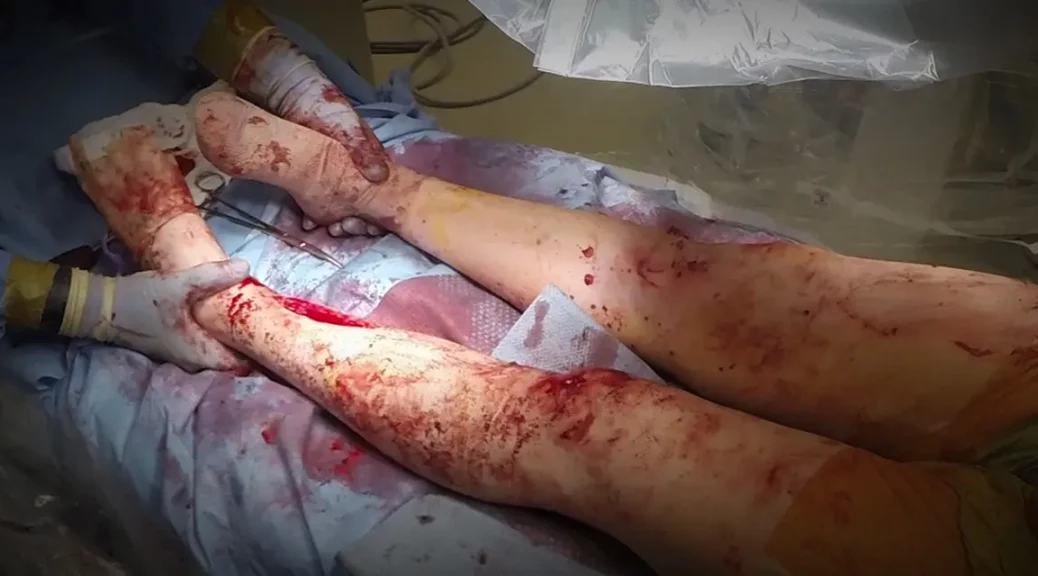
Left Tibia Pilon Open Fracture Open Reduction and Internal Fixation with External Fixator
Nelson Merchan, MD1,2; Andrew M. Hresko, MD1,2; Edward Kenneth Rodriguez, MD, PhD2
1Harvard Combined Orthopaedic Surgery Residency Program
2Beth Israel Deaconess Medical Center

Tibial plafond or pilon fractures account for 5 to 10% of all lower extremity fractures and are associated with high energy trauma. These fractures have a high rate of non-union, mal-union, and wound healing issues due to weak metaphyseal bone, a lack of robust soft tissue coverage, and complex intra-articular extension. This manuscript and video demonstrates a tibial pilon fracture managed acutely with a hybrid fixation approach combining internal fixation with external fixation.

PUBLISHED: Intramedullary Nail for Open Tibial Fracture

Intramedullary Nail for Open Tibial Fracture
Caleb P. Gottlich, MD, MS1; Michael J. Weaver, MD2
1Department of Orthopedic Surgery, Texas Tech University Health Science Center
2Brigham and Women’s Hospital

This article describes the stabilization of an open tibia shaft fracture using an intramedullary nail. After copious irrigation and debridement of the fracture site, a transpatellar tendon split is used to expose the nail entry point. This is followed by fracture reduction, sequential reaming, and nail insertion and locking. Finally, the technique for proximal tibia traction pin insertion is demonstrated on the contralateral tibia.

PUBLISHED: Left Hip Hemiarthroplasty for Femoral Neck Fracture

Left Hip Hemiarthroplasty for Femoral Neck Fracture
Michael Akodu, MBBS; Elyse J. Berlinberg, MD; Miles Batty, MD; Michael McTague, MPH; Kiran J. Agarwal-Harding, MD, MPH
Beth Israel Deaconess Medical Center

Hip fractures are a major cause of morbidity and mortality, especially among older patients. They also account for a significant portion of healthcare spending and other non-medical costs. These fractures can be classified into various types based on the parts of the femoral head and neck affected, and fixation options are dependent on both patient and injury characteristics. In this video, Dr. Agarwal-Harding takes us through a hip hemiarthroplasty for a left femoral neck fracture, highlighting various guiding principles and surgical considerations.

PUBLISHED: Closed Cephalomedullary Nailing of a Diaphyseal Femur Fracture on a Fracture Table

Closed Cephalomedullary Nailing of a Diaphyseal Femur Fracture on a Fracture Table
Sarita Jamil1; Michael J. Weaver, MD2
1University of Central Florida College of Medicine
2Brigham and Women’s Hospital

Femoral fractures typically occur in two major settings: high-energy mechanisms related to trauma and low-energy mechanisms in insufficiency fractures observed in elderly patients with osteopenia. Patients present with pain, swelling, and limited range of motion.

Intramedullary nailing is the definitive surgical treatment for femoral fractures to allow secondary healing of bone. Such a repair is performed here on a patient with a diaphyseal femoral fracture. Surgeon preference was to perform a closed cephalomedullary nailing with the patient supine on a radiolucent fracture table for traction.

PUBLISHED: Bimalleolar Ankle Fracture Open Reduction and Internal Fixation

Bimalleolar Ankle Fracture Open Reduction and Internal Fixation
Kiran J. Agarwal-Harding, MD, MPH; Michael Akodu, MBBS; Miles Batty, MD; Elyse J. Berlinberg, MD; Michael McTague, MPH
Beth Israel Deaconess Medical Center

Ankle injuries are common, occurring most often among young males and older females. The ankle joint is crucial for stability and gait, making these injuries a significant source of disability.

Ankle injuries are usually treated operatively when there is loss of joint congruity and stability, and in this video, Dr. Agarwal-Harding takes us through the operative fixation of a bimalleolar ankle fracture. He talks about understanding why operative intervention is recommended, techniques involved, and other considerations.

Right Distal Tibial Oblique Fracture Open Reduction and Internal Fixation (ORIF) with Medial Neutralization Non-locking Plate

Right Distal Tibial Oblique Fracture Open Reduction and Internal Fixation (ORIF) with Medial Neutralization Non-locking Plate
Andrew M. Hresko, MD; Edward Kenneth Rodriguez, MD, PhD
Beth Israel Deaconess Medical Center

Diaphyseal tibial fractures are common injuries that are most often treated with intramedullary nailing. However, certain patient factors may necessitate alternative treatment strategies such as open reduction internal fixation (ORIF) with plates and screws. Presence of a total knee arthroplasty (TKA) in the injured extremity is one such factor. TKA is a common operation that is only increasing in popularity, and management of tibia fractures distal to TKA may be a frequently encountered clinical scenario.

This video presents a technique for ORIF of a distal diaphyseal tibia fracture distal to a TKA that precludes intramedullary nail fixation. The fracture is fixed with lag screws and secured with an anatomically-contoured distal tibia locking-compression plate (LCP) in neutralization mode.

PUBLISHED: Open Reduction and Internal Fixation of Mandibular Body and Parasymphyseal Fractures with Maxillomandibular Fixation and Broken Tooth Extraction

Open Reduction and Internal Fixation of Mandibular Body and Parasymphyseal Fractures with Maxillomandibular Fixation and Broken Tooth Extraction
Derek Sheen, MD1; Cheryl Yu, MD2; Sarah Debs, MD2; Peter Kwak, MD2; Nima Vahidi, MD3; Daniel Hawkins, DDS2; Thomas Lee, MD, FACS2
1University of Texas Southwestern Medical Center
2Virginia Commonwealth University Medical Center
3Upstate Medical Center

This is a case discussing a 21-year-old male who suffered from both non-comminuted mandibular parasymphyseal and body fractures as a result of a motor vehicle accident, requiring open reduction internal fixation (ORIF) without postoperative maxillomandibular fixation (MMF). The fracture was complicated by a broken tooth root, which required extraction.

After intraoperative MMF, ORIF was performed. The parasymphyseal fracture was plated using two locking four-hole 2-mm thick miniplates utilizing two locking screws on either side of the fracture with one plate along the alveolar surface (monocortical screw) and one along the basal surface (bicortical screw). For the right body fracture, a three-dimensional locking ladder plate was used via a transbuccal trocar approach for additional exposure needed for proper screw placement. Once the hardware was secured, the patient was taken out of MMF and restoration of premorbid occlusion was confirmed. Lastly, watertight mucosal closure was performed using absorbable sutures and Dermabond (cyanoacrylate adhesive).

PUBLISHED: Open Reduction and Internal Fixation of a Diaphyseal Periprosthetic Humeral Fracture

Open Reduction and Internal Fixation of a Diaphyseal Periprosthetic Humeral Fracture
Ikechukwu C. Amakiri1; Michael J. Weaver, MD2
1Geisel School of Medicine, Dartmouth College
2Brigham and Women’s Hospital

Periprosthetic humeral shaft fractures are increasing in incidence as shoulder replacements become more common. Surgical management of humeral shaft fractures can only be deemed appropriate when the degree of pain, the extent of disability, and the number of comorbid conditions are taken into consideration.

Among trauma surgeons there exists no preferred surgical approach to fractures of different segments of the humerus; however, the anterolateral approach to midshaft fractures is the most common although viable alternative approaches exist. In this case, we perform an open reduction and internal fixation of a diaphyseal periprosthetic humeral fracture with a posterior triceps sparing approach.

PUBLISHED: Bone Graft for Nonunion of Right Thumb Proximal Phalanx Fracture

Bone Graft for Nonunion of Right Thumb Proximal Phalanx Fracture
Sudhir B. Rao, MD1; Mark N. Perlmutter, MS, MD, FICS, FAANOS2; Arya S. Rao3; Grant Darner4
1Big Rapids Orthopaedics
2Carolina Regional Orthopaedics
3Columbia University
4Duke University School of Medicine

In this video, the authors describe and demonstrate a surgical technique for the treatment of an unstable nonunion of a proximal phalangeal fracture of the thumb.

The video describes the surgical exposure, preparation of the nonunion site, harvesting of autogenous iliac corticocancellous bone graft, bone grafting of the defect, and stabilization with K-wire fixation.