Tag Archives: global surgery

PUBLISHED: Pediatric Supracondylar Humerus Fracture Repair with Mini-Open Assisted Reduction and Percutaneous Pinning

Pediatric Supracondylar Humerus Fracture Repair with Mini-Open Assisted Reduction and Percutaneous Pinning
Emily S. Powis, BS1; Donald L. Fejfar, MD1; Nikhil Gattu, MD1; Samhita Kadiyala, BA1; Elizabeth Rich, MD2; Wesley Kalomba, MD3; Hizkyas Kassaye, MD4; Ridwan M. Saeed, MD5; Bitiel Banda, MD6; Pierre M. Woolley, MD7; Kiran J. Agarwal-Harding, MD, MPH1,8
1Harvard Global Orthopaedics Collaborative, Boston, MA
2Walter Reed National Military Medical Center, Bethesda, MD
3Lilongwe Institute of Orthopaedics and Neurosurgery, Lilongwe, Malawi
4Hawassa University Comprehensive Specialized Hospital, Hawassa, Ethiopia
5Muhimbili Orthopaedic Institute, Dar es Salaam, Tanzania
6Mzuzu Central Hospital, Mzuzu, Malawi
7Hôpital Universitaire La Paix, Port au Prince, Haiti
8Beth Israel Deaconess Medical Center, Boston, MA

Supracondylar humerus (SCH) fractures are the most common elbow fractures in children and represent a significant source of morbidity in low- and middle-income countries (LMICs), where delayed presentation and limited surgical capacity frequently lead to poor outcomes. Closed reduction and percutaneous pinning (CRPP) is the gold-standard treatment for displaced SCH fractures and is particularly well-suited to resource-limited settings given its reliance on minimal, low-cost implants.

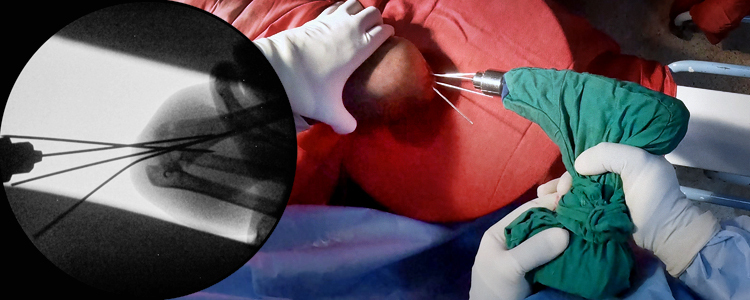
This case describes a 9-year-old male who presented to Mzuzu Central Hospital in Malawi with a completely displaced Gartland Type III SCH fracture following a fall. Surgical intervention was delayed three days due to unavailability of intraoperative fluoroscopic imaging. Neurovascular examination was intact on presentation. The procedure was performed under general anesthesia. Reduction was first attempted with longitudinal traction to unlock the distal fragment, followed by thumb pressure on the olecranon and elbow flexion. As the distal fragment remained incompletely reduced in the sagittal plane, a small posterior incision was made and the Kapandji maneuver was performed to achieve satisfactory reduction, confirmed fluoroscopically. Three smooth Kirschner wires (K-wires) were introduced in retrograde fashion from the lateral condyle under fluoroscopic guidance. One of the three K-wires was intramedullary and became loose prior to case conclusion, so it was removed before the remaining pins were cut and bent outside the skin, and a posterior back slab was applied with the elbow at 90 degrees of flexion. The remaining K-wires were removed at 4 weeks, and range-of-motion exercises were initiated thereafter.

This case demonstrates that percutaneous pinning, with mini-open assistance where closed reduction cannot be achieved, can be performed safely in resource-limited settings and illustrates the real-world intraoperative challenges, including limited C-arm resolution, use of non-orthopaedic drills with insufficient power, and bent K-wires, that afflict much of the developing world.
PUBLISHED: Anal Fistulotomy

Anal Fistulotomy
M. Grant Liska, BS¹; Marcus Lester R. Suntay, MD, FPCS, FPSPS, FPALES²
¹University of Central Florida College of Medicine
²Philippine Children’s Medical Center

Fistula-in-ano is a chronic abnormal communication between the anal canal and, usually, the perianal skin. It can be described as a hollow tract that is lined with granulation tissue and connects a primary opening inside the anal canal to a secondary opening in the perianal skin. It usually originates from the anal glands and is frequently the result of a previous anal abscess. Anal fistulae present with pain, swelling, pruritus, skin irritation, and purulent or bloody drainage. Most anal fistulae are diagnosed based on clinical findings, but complex and deep anal fistulae usually require imaging studies such as CT scan or MRI to delineate the tract.

Currently, there is no medical treatment available and surgery is almost always necessary. A simple intersphincteric fistula can often be treated with fistulotomy or fistulectomy, while trans-sphincteric and suprasphincteric fistulae are treated by placement of a seton to maintain drainage and induce fibrosis. Extrasphincteric fistula treatment depends on the anatomy and etiology of the fistula.

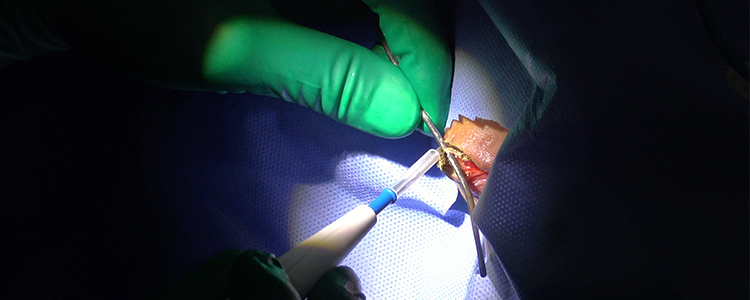
This article presents the case of a 1-year-old male with a history of recurrent perianal infection, which led to the development of an anal fistula. The anal fistula was noted to be superficial, and a fistulotomy was performed.

PUBLISHED: Sebaceous Cyst Excision

Sebaceous Cyst Excision
Casey L. Meier, RN¹; Marcus Lester R. Suntay, MD, FPCS, FPSPS, FPALES²
¹Lincoln Memorial University, DeBusk College of Osteopathic Medicine
²Philippine Children’s Medical Center

Sebaceous cysts are closed sacs filled with foul-smelling, cheese-like material found underneath the skin. They form when a gland or hair follicle becomes blocked and are commonly found on the scalp, face, neck, or torso. Sebaceous cysts are non-cancerous and usually present as painless lumps, but can become tender when infected.

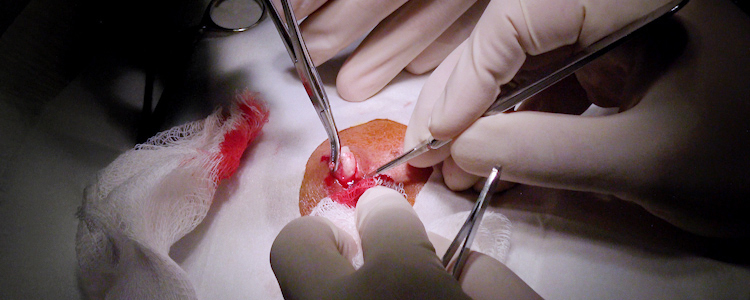
In most cases, smaller sebaceous cysts may be ignored as they do not cause any symptoms; however, larger cysts may need to be removed with complete excision recommended to prevent recurrence. Oral antibiotics may be required when a sebaceous cyst becomes infected. Here is the case of a 33-year-old male patient who underwent complete resection of a 2-year-old cyst.

PUBLISHED: Excision of Epidermal Inclusion Cyst

Excision of Epidermal Inclusion Cyst

John Grove
Lincoln Memorial University – DeBusk College of Osteopathic Medicine

Marcus Lester R. Suntay, MD, FPCS, FPSPS, FPALES
Philippine Children’s Medical Center

Epidermal inclusion cysts, also called keratin or epithelial cysts, are benign lumps that develop beneath the skin. They present as a slow-growing, painless lumps, usually with a punctum in the middle that represents the blockage of keratin excretion. Here, Dr. Lester Suntay with the World Surgical Foundation presents the case of a 64-year-old male with a mass on his upper back. It was noted to be gradually enlarging, and thus excision was performed in order to prevent further growth and infection.

JOMI Partners with InciSioN

JOMI is partnering with InciSioN (https://incisionetwork.org/).

InciSioN is a nonprofit organization representing over 5000 students, trainees, and early career physicians around the world, who are passionate about Global Surgery. We work towards the common goal of access to safe, timely and affordable surgical healthcare for all. Our work rests on three pillars of Advocacy, Education, and Research.

PREPRINT RELEASE: Colonic Interposition for Esophageal Atresia

Colonic Interposition for Esophageal Atresia
Mario Catarino Rivas Hospital, Honduras

Yoko Young Sang, MD
Resident Physician
General Surgery
Louisiana State University Shreveport

Caroll Alvarado Lemus, MD
Pediatric Surgery, Mario Catarino Rivas Hospital, Honduras
San Pedro Sula, Honduras

Domingo Alvear, MD
Founder
World Surgical Foundation

The patient in this case is a 6-year-old boy who was born with Down syndrome and esophageal atresia. In this video article, Dr. Alvear performs a colonic interposition to replace the absent esophagus with part of the patient’s colon. This was performed during a global surgical mission in Honduras with the World Surgical Foundation.

PREPRINT RELEASE: Left Mastectomy Wound Closure with Left Latissimus Dorsi Musculocutaneous Local Flap

Left Mastectomy Wound Closure with Left Latissimus Dorsi Musculocutaneous Local Flap
Hospital Leonardo Martinez, Honduras

Geoffrey G. Hallock, MD
Plastic Surgery Consultant
Sacred Heart Campus, St. Luke’s Hospital
Allentown, Pennsylvania

Yoko Young Sang, MD
Resident Physician
General Surgery
Louisiana State University Shreveport

In this case, Dr. Hallock closes the wound that was left behind following a mastectomy using a latissimus dorsi musculocutaneous local flap. This was performed during a surgical mission in Honduras with the World Surgical Foundation.

PREPRINT RELEASE: Abdominal Hysterectomy for Uterine Fibroids

Abdominal Hysterectomy for Uterine Fibroids
Hospital Leonardo Martinez, Honduras

Col. Arthur C. Wittich, DO
Fort Belvoir Community Hospital (Retired)
World Surgical Foundation

In this case, Dr. Wittich performs an abdominal hysterectomy on a 45-year-old female with symptomatic uterine fibroids. This was performed during a surgical mission in Honduras with the World Surgical Foundation.

PREPRINT RELEASE: Intraperitoneal Mesh Repair for Incisional Hernia

Intraperitoneal Mesh Repair for Incisional Hernia
Hospital Leonardo Martinez, Honduras

Yoko Young Sang, MD
Resident Physician
General Surgery
Louisiana State University Shreveport

Shabir Abadin, MD, MPH (Operating Surgeon)
Endocrine and General Surgeon
World Surgical Foundation

The patient in this case had an emergency exploratory laparotomy and diverting colostomy several years ago for a perforated colon. Following reversal of the colostomy, she developed an incisional hernia that also involved the stomal site. Here, Dr. Abadin performs an intraperitoneal mesh repair while on a surgical mission in Honduras with the World Surgical Foundation.

PREPRINT RELEASE: Blind Technique for Subclavian Central Line Placement

Blind Technique for Subclavian Central Line Placement
St. Catarina Hospital, Honduras

Domingo Alvear, MD
Founder, World Surgical Foundation

Caroll Alvarado Lemus
Pediatric Surgery, Hospital Mario Catarino Rivas
San Pedro Sula, Honduras

Yoko Young Sang, MD
Resident Physician
General Surgery
Louisiana State University Shreveport

This case demonstrates a blind technique used for subclavian central line placement when imaging is not available. It was performed in Honduras on a surgical mission with the World Surgical Foundation in a resource-poor environment.